



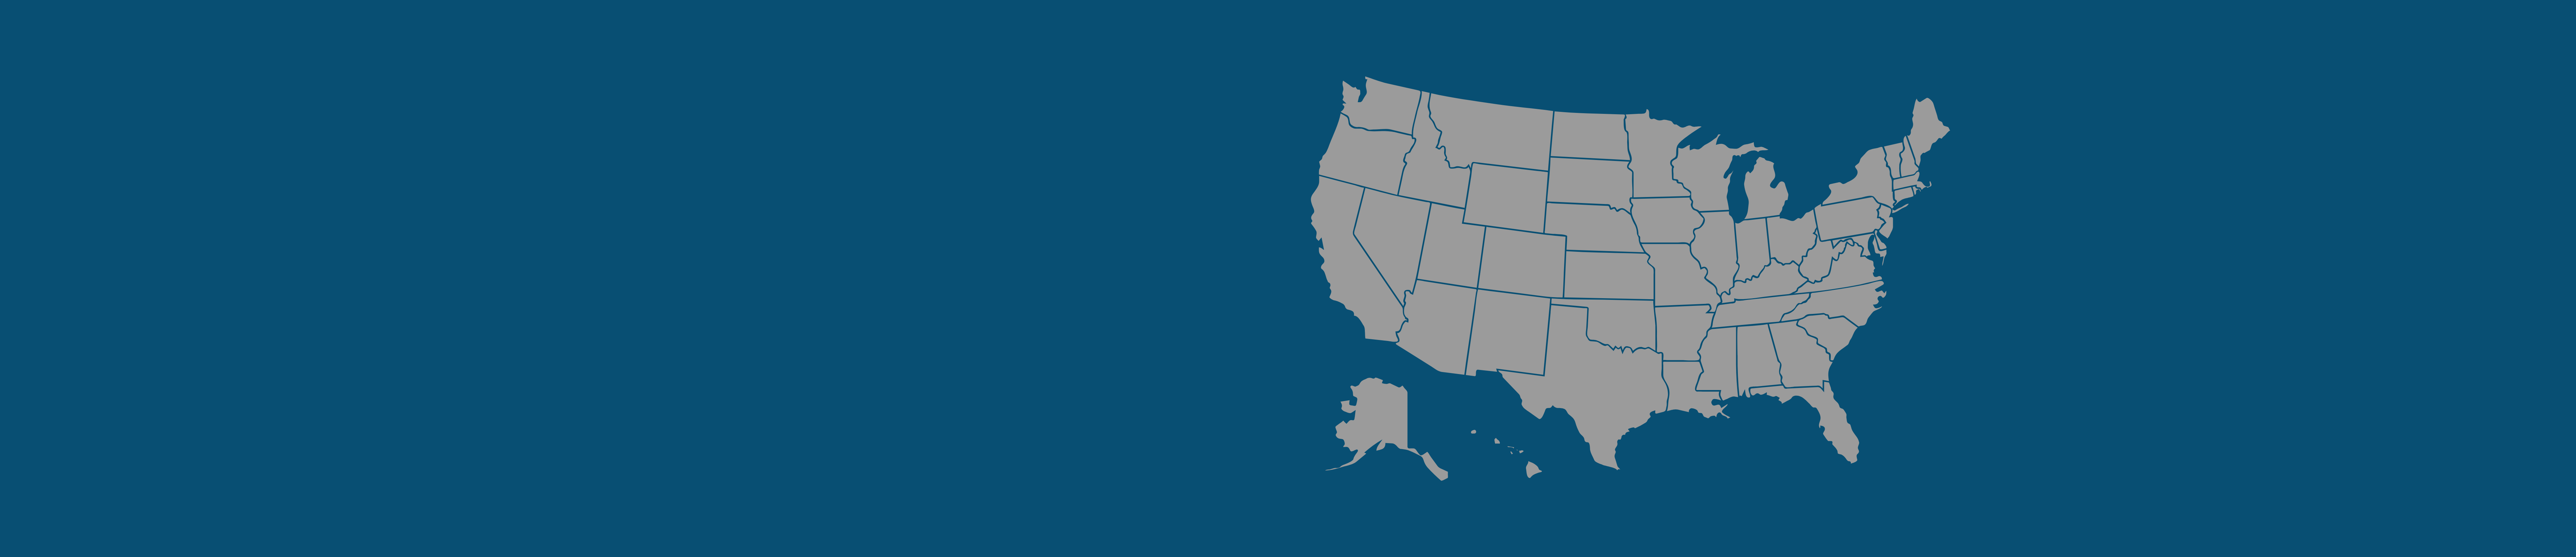
Where a CRNA chooses to practice can shape their day-to-day autonomy as much as their specialty or setting does. But “independent practice” gets used loosely, and that can cost CRNAs real information when they’re comparing offers. Here’s what independent practice actually means, which states currently allow it, and how to factor scope of practice into your career decisions.
What “Independent Practice” Actually Means for CRNAs
The phrase “CRNA independent practice” usually gets applied to a single list: the states that have opted out of a federal Medicare rule.
In November 2001, CMS finalized a rule requiring physician supervision of CRNAs as a condition of Medicare and Medicaid reimbursement. States can opt out if the governor attests to CMS that doing so serves the state’s citizens and is consistent with state law. Once CMS accepts that, physician supervision is no longer a condition of Medicare reimbursement there.
That’s the entire scope of what opting out does. It doesn’t rewrite a state’s nurse practice act or override a hospital’s bylaws, which is why “opt-out state” and “independent practice state” aren’t quite the same thing. Opt-out status is a necessary piece of the picture for Medicare-billed care, but not the whole picture.
The Current List of CRNA Opt-Out States
As of 2026, 27 states have opted out of the federal physician-supervision requirement. Iowa was first, opting out in December 2001. Vermont and Ohio are the most recent state additions, both opting out in July 2026 while Washington D.C. is the latest U.S. Jurisdiction to opt out in September 2026.
| U.S. Jurisdiction/State | Opt-Out Date |
|---|---|
| Iowa | December 2001 |
| Nebraska | February 2002 |
| Idaho | March 2002 |
| Minnesota | April 2002 |
| New Hampshire | June 2002 |
| New Mexico | November 2002 |
| Kansas | March 2003 |
| North Dakota | October 2003 |
| Washington | October 2003 |
| Alaska | October 2003 |
| Oregon | December 2003 |
| Montana | January 2004 |
| South Dakota | March 2005 |
| Wisconsin | June 2005 |
| California | July 2009 |
| Colorado | September 2010 |
| Kentucky | April 2012 |
| Arizona | March 2020 |
| Oklahoma | August 2020 |
| Utah | February 2022 |
| Michigan | May 2022 |
| Arkansas | May 2022 |
| Wyoming | May 2023 |
| Delaware | June 2023 |
| Massachusetts | June 2024 |
| Vermont | July 2026 |
| Ohio | July 2026 |
| U.S. Jurisdiction Alone | |
| Washington D.C. | September 2026 |
Guam has also opted out, though as a territory rather than a U.S Jurisdiction, it’s tracked separately from the 27-state count.
Opt-out status only describes Medicare billing rules — it doesn’t guarantee a CRNA can practice without a supervising physician, dentist, or podiatrist in every hospital or setting, since individual facilities can maintain stricter anesthesia care team requirements. If you’re weighing a move to one of these states, the APEX Job Board is worth browsing early, to see how that plays out in actual job postings.
How State Scope-of-Practice Law Differs From Medicare Opt-Out Status
If opt-out status is one layer, a state’s own scope-of-practice law is a second, separate layer — the one that actually defines what a CRNA is legally permitted to do in that state, for any patient, regardless of payer.
Scope of practice is set not only by each state’s nurse practice act and board of nursing rules,but in some states, the board of medicine may also play a role (i.e. Virginia) covering what opt-out status doesn’t — like whether a CRNA can administer anesthesia without a collaborative agreement, or order diagnostics and manage a patient’s airway without physician sign-off. A third layer sits on top of both: institutional bylaws and malpractice requirements. A hospital’s bylaws can require an anesthesia care team model even in a state that’s opted out and grants broad scope-of-practice authority; malpractice carriers can build similar expectations into their underwriting.
Because these layers move independently, two opt-out states can look very different day to day: one might pair permissive scope-of-practice law with mostly CRNA-only staffing, while another stays dominated by anesthesia care team models despite also being opted out.
Practicing in Non-Opt-Out States: What Changes
In the roughly half of states that haven’t opted out, physician supervision remains a condition of Medicare and Medicaid reimbursement for CRNA-delivered anesthesia — a supervising physician needs to be involved for those services to be billed. That’s a billing requirement, though, not a description of clinical autonomy: a CRNA in a non-opt-out state can still have significant hands-on responsibility for case management and intraoperative decision-making, depending on the setting and how “supervision” is structured in practice.
How Independent Practice Affects CRNA Career Decisions
For CRNA students and practicing CRNAs weighing where to work, the opt-out map is a starting point for research, not a final answer.
Autonomy and Scope of Daily Responsibilities
Your actual independence depends on the combination of opt-out status, state scope-of-practice law, and the facility’s staffing model — not any one alone. A CRNA-only role in a rural hospital can offer more autonomy than an anesthesia care team role in a state that’s technically opted out, so look at how the specific facility staffs anesthesia before assuming the state’s status describes the job.
Compensation and Job Market Considerations
Markets with more CRNA-only practice models tend to have different staffing ratios, call expectations, and pay structures than markets with anesthesia care teams — and which model a given opening uses matters more than the state’s opt-out status alone. APEX Anesthesia’s CRNA Career Report, built from a survey of more than 600 practicing CRNAs, breaks down how compensation, contract type, and autonomy expectations vary by practice setting.
How to Evaluate a State’s Practice Environment Before You Take a Job
Checking a state’s opt-out status is a reasonable first filter, but it shouldn’t be the last question you ask. Before accepting a position or planning a relocation, dig into the state’s nurse practice act and board of nursing rules (separate from Medicare billing rules); the specific facility’s staffing model and bylaws — CRNA-only, care team, or a mix; malpractice coverage terms and whether the employer’s policy requires supervision beyond what state law mandates; and how the environment has trended recently, since a newly opted-out state like Vermont or Ohio may still have facilities adjusting staffing to match. The AANA’s fact sheet on state opt-outs and each state’s board of nursing are the two primary sources worth checking directly, since both change as states act.
Whatever state you end up practicing in, the scope and supervision rules will shape your role, but so will how well you know your material. APEX Anesthesia Review’s Student Review Course, built by CRNAs for CRNAs, helps you master the content you need to pass your certification exam and walk into your first day on the job with confidence. Check out our Student Review demo!
Related Articles


